Knee Deformity & Malalignment Treatment in Bangalore
Standing in front of a mirror, you notice it — your knees bend inward or bow outward. Shoes wear unevenly on one side. And over time, the pain has crept in: a dull ache on one side of the knee that gets worse with walking, climbing stairs, or simply standing for long periods.
Knee malalignment — whether varus (bow legs) or valgus (knock knees) — isn’t just a cosmetic concern. When your leg’s mechanical axis shifts, the load distribution across the knee joint changes. One side of the joint bears more pressure than the other, and over years, this can accelerate cartilage wear, meniscal damage, and osteoarthritis. Rotational deformities — where the femur or tibia is twisted — can cause similar problems, often leading to patellar instability and gait dysfunction. At our clinic in Bangalore, Dr. Raghavendra Kembhavi takes a biomechanical approach to knee realignment, focusing on restoring proper load distribution and preserving your natural joint for the long term.
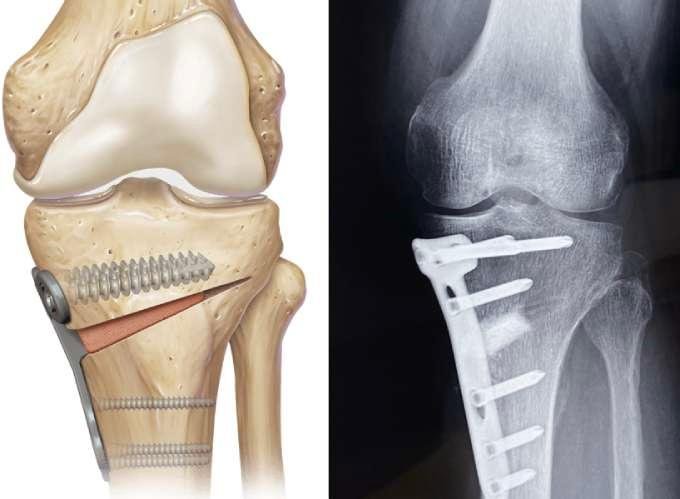
What causes knee malalignment?
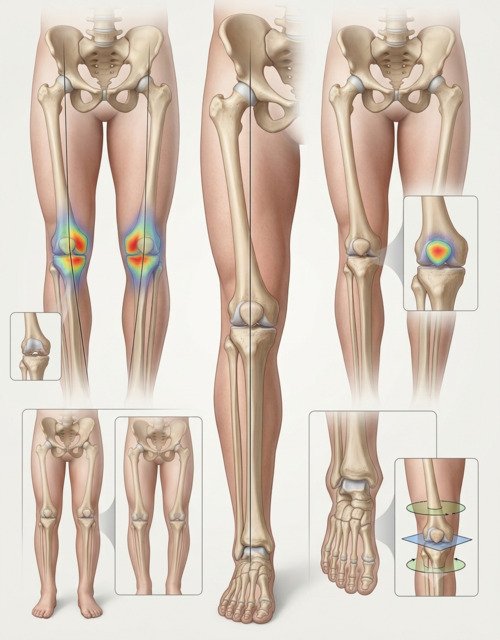
Knee alignment is determined by the shape of your femur, tibia, and the angle at which they meet. In a well-aligned leg, the mechanical axis runs from the centre of the hip through the centre of the knee to the centre of the ankle. When this line shifts, the load distribution changes — and the consequences follow.
Varus deformity (bow legs) shifts the mechanical axis medially, placing excessive load on the inner (medial) compartment of the knee. This is the more common deformity in adults with osteoarthritis. Valgus deformity (knock knees) shifts the axis laterally, overloading the outer (lateral) compartment. Rotational deformities — excessive femoral anteversion or tibial torsion — alter the tracking of the patella and the mechanics of gait, often causing anterior knee pain and instability.
The causes vary. In children, mild bow legs and knock knees are part of normal development and usually resolve spontaneously. But when the deformity persists or worsens, conditions like Blount’s disease, rickets, or a physeal bar should be considered. In adults, malalignment can result from childhood deformities that were never corrected, previous fractures that healed in poor position, metabolic bone disease, or degenerative changes that have gradually altered the joint’s alignment.
Signs and symptoms
Knee malalignment can be visible from the outside, but the symptoms are what bring most patients to the clinic. The pattern often points to the type and severity of the deformity.
Visible deformity
Bow legs (knees apart, ankles together) or knock knees (knees together, ankles apart) that are noticeable when standing.
One-sided knee pain
Pain concentrated on the inner side (varus) or outer side (valgus) of the knee, often worse with activity.
Uneven shoe wear
Shoes wearing out faster on the inner or outer edge, reflecting the altered load distribution through the leg.
Gait abnormalities
A varus or valgus thrust during walking, or an in-toeing/out-toeing pattern from rotational deformity.
Diagnosis
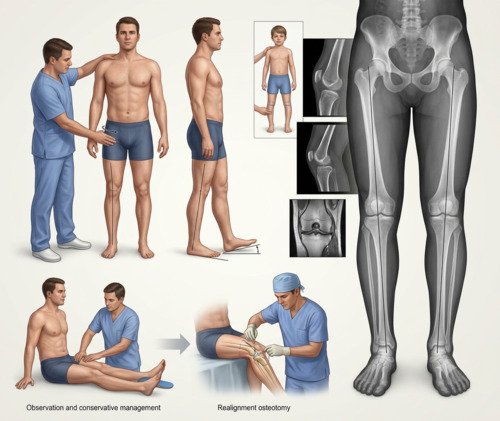
Diagnosis begins with a detailed history and physical examination. Dr. Kembhavi will assess your standing alignment, gait pattern, and rotational profile — measuring hip rotation, thigh-foot axis, and foot progression angle to identify the exact location and type of deformity. Standing full-length X-rays of both legs are essential to measure the mechanical axis and determine the degree of malalignment.
Imaging and assessment
Standing full-length X-rays are the gold standard — they show the mechanical axis and allow precise measurement of the deformity. CT rotational profile is used when rotational deformity is suspected, measuring femoral anteversion and tibial torsion. MRI may be ordered to assess associated cartilage, meniscal, or ligament injuries. In children, growth remaining is an important consideration, and the physis must be evaluated.
Treatment approach
Treatment depends on the type and severity of the deformity, your age, and whether there’s associated arthritis. Mild deformities in children often resolve spontaneously and require only observation. In adults, conservative management — physiotherapy, orthotics, weight management — can reduce symptoms but doesn’t correct the underlying alignment. Realignment osteotomy is the surgical option for symptomatic malalignment, redistributing load away from the overloaded compartment. The choice between femoral, tibial, or combined osteotomy depends on where the deformity originates.
How knee malalignment is treated
Step 1
Biomechanical Assessment
Detailed evaluation of alignment, gait, and rotational profile. Standing X-rays to measure the mechanical axis and plan correction.
Step 2
Conservative Management
Physiotherapy to strengthen supporting muscles, orthotic insoles to offload the affected compartment, and activity modification.
Step 3
Growth Modulation (Children)
In growing children, guided growth procedures using tension-band plates can gradually correct the deformity while preserving growth potential.
Step 4
Realignment Osteotomy
Surgical correction of the deformity — either at the femur, tibia, or both — to restore the mechanical axis and redistribute load.
Step 5
Rotational Correction
For torsional deformities, derotational osteotomy of the femur or tibia can restore normal rotational alignment and improve gait mechanics.
Step 6
Structured Rehabilitation
A phased programme to restore strength and function, with weight-bearing restrictions and progressive return to activity.
Conservative vs. Surgical Realignment
| Factor | Conservative Management | Realignment Osteotomy |
|---|---|---|
| Best for | Mild deformity, early symptoms, low-demand patients | Significant deformity, progressive arthritis, active patients |
| Effect on alignment | Does not correct deformity; manages symptoms | Directly corrects the mechanical axis |
| Joint preservation | Slows progression by reducing load | Redistributes load to preserve the joint and delay replacement |
| Recovery time | No downtime; ongoing therapy | Protected weight-bearing 6–8 weeks; full recovery 4–6 months |
Why choose Dr. Raghavendra Kembhavi
Biomechanical approach to realignment
Knee malalignment isn’t just about the knee — it’s about the entire limb. Dr. Kembhavi assesses the hip, knee, and ankle alignment together, identifying the exact site of the deformity and planning correction accordingly.
Joint preservation is the goal
Realignment osteotomy redistributes load away from the damaged compartment, preserving the natural joint and delaying or preventing the need for knee replacement. This is particularly valuable for younger, active patients.
Individualised treatment planning
Not every deformity needs surgery. Dr. Kembhavi carefully assesses the severity of malalignment, the presence of arthritis, and your functional goals to determine the most appropriate treatment path.
Comprehensive lower limb assessment
Knee malalignment can originate anywhere along the limb. Dr. Kembhavi evaluates the entire lower limb — including hip rotation, femoral version, tibial torsion, foot progression, and gait — rather than focusing only on the knee. Standing full-length X-rays assess the mechanical axis, while CT rotational profiling is used when torsional deformity is suspected. This whole-limb assessment identifies the true source of the deformity, ensuring realignment corrects abnormal loading and provides lasting results.
Recovery timeline after osteotomy
Recovery from osteotomy requires patience. The bone needs time to heal, and weight-bearing is progressed gradually to protect the fixation.
Weeks 0–6: Protection
Crutches and protected weight-bearing. Focus on reducing swelling and gentle range of motion. Bone healing begins.
Weeks 6–12: Partial Weight-Bearing
Gradual progression to full weight-bearing as bone healing progresses. Physiotherapy continues with range of motion and light strengthening.
Months 3–6: Strengthening
Progressive strengthening and functional training. Return to daily activities and low-impact exercise.
Month 6+: Return to Activity
Full return to activity and sport, guided by strength and functional testing. Ongoing monitoring of alignment and joint health.