Meniscus Root Tear Treatment in Bangalore
Meniscus root tears are among the most serious knee injuries — yet they’re frequently missed. Unlike a standard meniscus tear, a root tear happens right at the anchor point where the meniscus attaches to the bone. When that anchor fails, the meniscus loses its ability to distribute load, and the knee effectively behaves as if the entire meniscus has been removed.
What makes this injury particularly concerning is its silent nature. Many patients never experience the classic locking or catching associated with meniscus tears. Instead, there’s a vague posterior knee pain, intermittent swelling, and a gradual decline in function. Left untreated, root tears can lead to rapid cartilage loss and early osteoarthritis within just a few years. At our clinic in Bangalore, Dr. Raghavendra Kembhavi specialises in arthroscopic root repair — a joint-preserving procedure that restores the meniscus anchor and protects the knee for the long term.
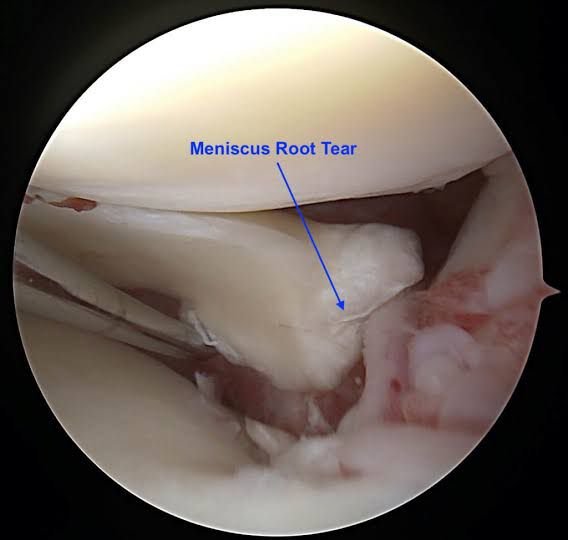
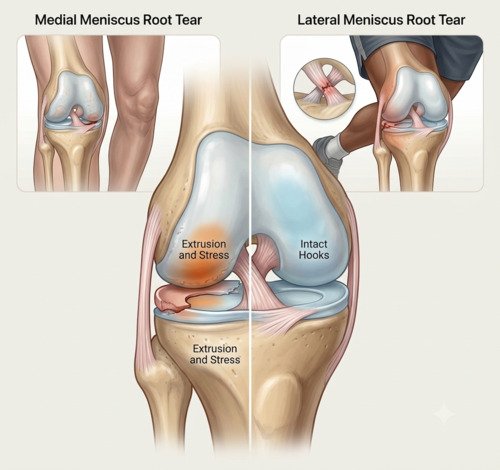
What is a meniscus root tear?
Each meniscus is anchored to the shin bone at two points — the anterior and posterior roots. These roots are like the ends of a rope tied to a post. They maintain the meniscus in its proper position and allow it to distribute load across the knee joint.
When a root tears, the meniscus can no longer function as a shock absorber. Biomechanically, it’s equivalent to removing the entire meniscus — the joint is exposed to significantly increased contact pressures, and cartilage damage begins to accelerate. This is why early diagnosis and treatment matter so much.
Root tears fall into two main categories. Medial root tears are more common and typically occur in middle-aged and older adults, often with minimal trauma or no specific injury at all. They’re associated with degenerative changes and varus alignment (bow-legged). Lateral root tears are less common and often occur alongside ACL injuries, particularly in younger, active patients.
Signs and symptoms
Root tears are notoriously difficult to diagnose because their symptoms overlap with many other knee conditions. A recent study of over 200 patients found that most present with an effusion, a positive McMurray test, and a positive hyperflexion test.
Posterior knee pain
Deep pain at the back of the knee, often worsened by squatting, kneeling, or deep flexion.
Intermittent swelling
Effusion is present in approximately 71% of patients, often developing hours after activity.
Difficulty with deep knee bending
A positive hyperflexion test is found in over half of patients — pain when the knee is bent beyond 90 degrees.
A pop at the time of injury
About 39% of patients report hearing or feeling a pop, usually after a low-energy twisting injury.
Diagnosis
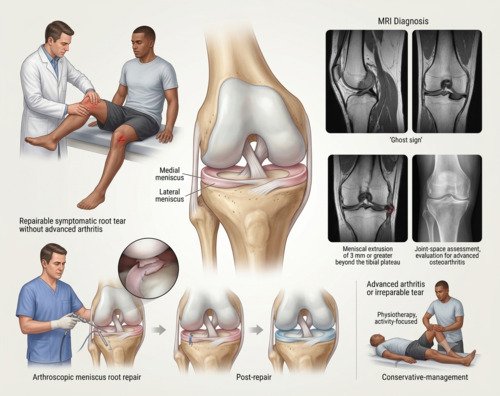
Diagnosis begins with a detailed history and physical examination. Dr. Kembhavi will look for specific signs — a positive McMurray test, tenderness at the joint line, and pain with deep knee flexion. An MRI is the gold standard for confirmation, with hallmark findings including the sagittal “ghost sign” and coronal truncation of the posterior horn. Importantly, root tears can be easily missed on standard MRI, so a high index of suspicion is essential.
Imaging and assessment
An MRI is essential for diagnosis. Key findings include the sagittal ghost sign (absence of the normal meniscal root on sagittal images), coronal truncation, and meniscal extrusion of 3mm or more. X-rays help assess joint space and rule out advanced arthritis, which can influence treatment decisions. In some cases, a diagnostic arthroscopy may be needed to directly visualise the root and confirm repairability.
Treatment approach
Treatment depends on the tear’s characteristics, your age, and the health of the joint. For symptomatic root tears without advanced arthritis, surgical repair is generally recommended and should be performed early — ideally within 3 months of symptom onset. Repair restores the meniscal anchor, reduces extrusion, and has been shown to significantly lower the risk of arthritis progression compared to conservative management. For patients with advanced arthritis or irreparable tears, non-surgical management or alternative procedures may be more appropriate.
How meniscus root tears are treated
Step 1
Diagnosis & Planning
MRI confirms the diagnosis. Dr. Kembhavi assesses the tear pattern, joint health, and alignment to determine if repair is appropriate.
Step 2
Pre-operative Preparation
Physiotherapy to restore motion and reduce swelling. Education on the strict non-weight-bearing protocol that will follow surgery.
Step 3
Arthroscopic Root Repair
Keyhole surgery to reattach the torn root to its anatomical footprint using sutures passed through a bone tunnel.
Step 4
Centralization (If Needed)
If the meniscus is significantly extruded, additional fixation to the meniscotibial ligament helps restore its position and function.
Step 5
Strict Rehabilitation
Strict non-weight-bearing for 6 weeks to protect the repair. A phased programme restores motion and strength.
Step 6
Return to Activity
Gradual return to daily activities and, for some patients, sport. Full recovery typically takes 4–6 months.
Repair vs. conservative management
| Factor | Surgical Repair | Conservative Management |
|---|---|---|
| Best for | Symptomatic tears, no advanced arthritis | Advanced arthritis, low-demand patients |
| Pain relief | Significant improvement in pain and function scores | Symptom management only |
| Arthritis progression | Slows progression; preserves joint | Does not stop progression |
| Recovery time | Strict non-weight-bearing 6 weeks; full recovery 4–6 months | No downtime; guided by symptoms |
Why choose Dr. Raghavendra Kembhavi
Early repair gives the best results
Timing is critical with root tears. Repair within 3 months of symptom onset gives the best chance of preserving the joint and preventing irreversible cartilage damage. Dr. Kembhavi prioritises prompt assessment and treatment.
Advanced arthroscopic techniques
Dr. Kembhavi uses the latest arthroscopic techniques for root repair, including transtibial pull-out and suture anchor fixation. When indicated, centralization can further improve outcomes by reducing meniscal extrusion.
Accurate diagnosis matters
Root tears are frequently missed — one study found that approximately 33% are undetected on standard MRI. Dr. Kembhavi’s careful assessment and high index of suspicion ensure the diagnosis is made and treatment is not delayed.
Comprehensive knee assessment
Root tears often occur with other knee injuries. Dr. Kembhavi’s thorough diagnostic process identifies associated ligament or cartilage damage, ensuring they’re addressed in the same treatment plan.
Recovery timeline after root repair
The recovery protocol after root repair is strict. The repair cannot take load until it has healed, and this is the single most important instruction in the protocol.
Weeks 0–6: Strict Non-Weight-Bearing
Crutches, brace locked in extension. No weight through the leg. Focus on quadriceps activation and full extension.
Weeks 6–9: Partial Weight-Bearing
50% weight-bearing with crutches. Gait retraining. Stationary bike as range allows.
Weeks 9–12: Full Weight-Bearing
Wean off crutches as gait normalises. Progressive strengthening, avoiding deep loaded flexion.
Months 3–6: Return to Activity
Restrictions on deep flexion and twisting lift after 3 months. Impact loading and running begin when strength criteria are met, usually 4–6 months.