Meniscal Injuries Treatment in Bangalore
You twisted your knee getting up from a chair, or maybe it happened during a game. Now there’s a catching sensation on the inside of your knee, some swelling, and it doesn’t quite feel stable when you put weight on it. This is often how a meniscal injury presents.
The meniscus is a piece of cartilage that acts as a shock absorber in your knee, distributing load and protecting the joint surface. When it tears, it can cause pain, catching, and stiffness. Some tears heal on their own; others need surgery. At our clinic in Bangalore, Dr. Raghavendra Kembhavi takes a tailored approach to meniscal injuries — preserving as much of the meniscus as possible, because every millimetre matters for the long-term health of your knee.
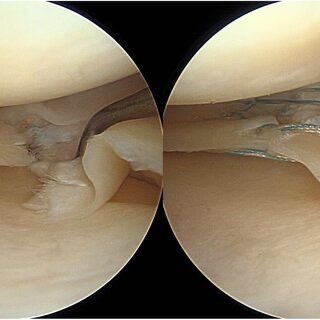
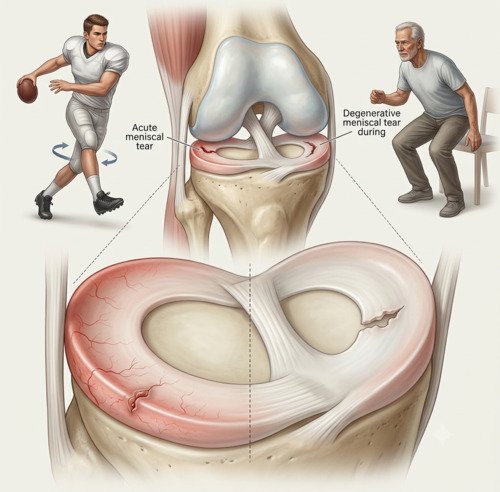
What causes meniscal injuries?
Each knee has two menisci — one on the inner side (medial) and one on the outer side (lateral). They’re made of tough fibrocartilage and serve two main purposes: they act as shock absorbers and they deepen the knee joint to improve stability.
Meniscal tears happen in two main ways. Traumatic tears occur during sports when you twist your knee while your foot is planted — common in football, basketball, and skiing. These often happen in younger, active people. Degenerative tears develop gradually as the meniscus weakens with age. These can happen with minimal trauma — sometimes just getting up from a chair or squatting down.
The location of the tear matters. The outer third of the meniscus has a blood supply (the “red zone”) and can heal. The inner two-thirds (the “white zone”) has no blood supply and cannot heal on its own. This is why some tears respond to conservative treatment while others need surgical repair.
Signs and symptoms
Meniscal tears produce a fairly characteristic set of symptoms. The pattern often points to the diagnosis before any imaging is done.
Pain along the joint line
A sharp or aching pain on the inner or outer side of the knee, often made worse by twisting or squatting.
Catching or locking
A sensation that something is caught inside the knee, especially with certain movements. The knee may briefly lock.
Swelling
The knee may swell within 24–48 hours of the injury, though degenerative tears may cause intermittent swelling.
Difficulty squatting or twisting
Movements that involve deep knee bending or rotation often reproduce the pain and catching sensation.
Diagnosis
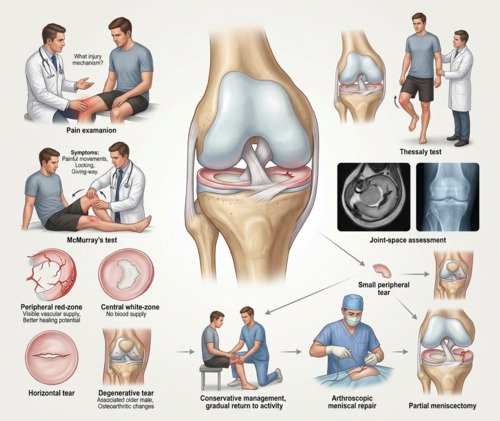
Diagnosis begins with a detailed history — how the injury happened, what movements bring on the pain, and whether there’s been any locking or giving way. Dr. Kembhavi then performs specific tests — McMurray’s test and the Thessaly test are the most reliable — to reproduce the pain and identify the tear location. An MRI confirms the diagnosis and shows the size, pattern, and location of the tear, which guides the treatment decision.
Imaging and confirmation
An MRI is the imaging study of choice. It shows whether the tear is in the red zone (peripheral, with blood supply) or the white zone (central, avascular), and whether it’s a simple horizontal tear or a complex degenerative pattern. X-rays are useful to assess the joint space and rule out arthritis, which can change the treatment approach. In older patients, the presence of arthritis alongside a meniscal tear affects the decision between repair and conservative management.
Treatment approach
Treatment depends on the tear’s location, size, and pattern, your age, and your activity level. Small peripheral tears in the red zone often heal with conservative treatment — rest, physiotherapy, and gradual return to activity. Larger tears, or those causing mechanical locking, usually need surgery. The goal is always to preserve as much meniscus as possible. Repair is preferred when the tear is in a vascular zone and suitable for suturing. Partial meniscectomy (removing only the torn portion) is reserved for tears that cannot be repaired. Total meniscectomy is rarely performed today because it leads to early arthritis.
How meniscal injuries are treated
Step 1
Immediate Care
Rest, ice, compression, and elevation for the first 48–72 hours to reduce pain and swelling.
Step 2
Diagnostic MRI
Confirms the location, size, and pattern of the tear. Determines whether the tear is repairable.
Step 3
Conservative Care
Physiotherapy to strengthen the quadriceps and hamstrings, activity modification, and anti-inflammatory medications.
Step 4
Arthroscopic Surgery
Keyhole surgery to repair the tear or remove the torn portion. The goal is to preserve as much meniscus as possible.
Step 5
Structured Rehabilitation
A phased programme to restore range of motion, strength, and function, with clear milestones for progression.
Step 6
Return to Activity
Gradual return to daily activities and sport, guided by strength, comfort, and functional testing.
Repair vs. removal vs. conservative treatment
| Factor | Repair | Partial Meniscectomy | Conservative |
|---|---|---|---|
| Best for | Peripheral tears in red zone, younger patients | Degenerative or irreparable tears | Small stable tears, low-demand patients |
| Long-term joint health | Preserves meniscus; best for preventing arthritis | Removes torn tissue; some risk of arthritis | Preserves meniscus if tear heals |
| Recovery time | Longer — crutches and bracing 4–6 weeks | Quicker — walking within days, full recovery 4–6 weeks | No downtime; guided by symptoms |
| Return to sport | 4–6 months | 6–12 weeks | Variable; depends on healing |
Why choose Dr. Raghavendra Kembhavi
Meniscus preservation is the priority
Every millimetre of meniscus matters for long-term knee health. Dr. Kembhavi always aims to repair rather than remove when the tear is suitable, because preserving the meniscus reduces the risk of early arthritis.
Arthroscopic expertise
When surgery is needed, Dr. Kembhavi performs meniscal surgery arthroscopically through small keyhole incisions. This allows precise visualisation of the tear and repair or removal with minimal disruption to surrounding tissues.
Individualised treatment decisions
Not every meniscal tear needs surgery. Dr. Kembhavi carefully assesses the tear pattern, location, and your activity level — because a small stable tear in a low-demand patient may do well with conservative care.
Comprehensive knee assessment
Meniscal tears often occur alongside other knee injuries. Dr. Kembhavi’s thorough diagnostic process identifies associated ligament or cartilage damage, ensuring they’re addressed in the same treatment plan.
Recovery timeline after meniscal surgery
Recovery depends on whether the meniscus is repaired or removed. Repair requires protection while the tissue heals; removal allows faster return to activity.
Week 0–2: Protection
Crutches and possibly a brace (for repair). Focus on reducing swelling and gentle range of motion.
Week 2–6: Motion & Strengthening
Progressive range of motion and strengthening. Crutches discontinued (for meniscectomy), or partial weight-bearing (for repair).
Week 6–12: Functional Training
Advanced strengthening, balance training, and low-impact activities. Running may begin for meniscectomy patients.
Month 3+: Return to Sport
Return to sport for meniscectomy patients (6–12 weeks) or repair patients (4–6 months), guided by strength testing.